
Blepharochalasis Syndrome
Updated September 2026
Establishing the diagnosis
Etiology
- Recurrent periorbital swelling, beginning in adolescence, causing progressive loss of elasticity, periorbital skin redundancy, and lacrimal gland prolapse
- IgA-mediated autoimmune process, with IgA deposits around the remaining elastin fibers and blood vessels (Wang, Arch Dermatol 2009)
- Dermatochalasis is a term restricted to involutional change, with skin redundancy, frequently confused with blepharochalasis, a term specifically describing this condition of recurrent edema in adolescents (Tenzel, Arch Ophthalmol 1978).
Epidemiology
- Although uncommon, several case series have been reported.
- In 54 cases from Beijing, average age at onset was 9.3 years, duration of clinical disease was 2–16 years, stabilizing in later adolescence (Li, Chinese J Ophthalmol 2012).
- In 30-patient series from Moorfields, age of onset ranged from 2.5-40 years, duration of disease from 4-37 years. The disease was staged between active (early) stage and quiescent (late) stage; blepharochalasis is likely localized angioedema (Collin, OPRS 1991)
- Most cases are sporadic, but some can show autosomal dominant inheritance.
- Female:male ratio is about about 3:2 (Koursh, Surv Ophthal 2009).
History
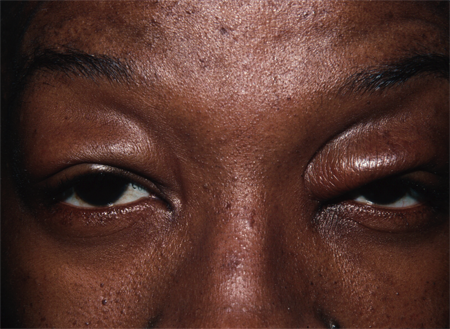
Figure 1. Blepharochalasis. Courtesy Rona Z. Silkiss, MD, FACS.
- History more than physical exam helps establish the diagnosis with recurrent painless eyelid swelling, starting in adolescence, and poor response to antihistamine therapy (Wang, Arch Dermatol 2009).
- Primarily upper lids, but lower eyelids may be involved.
- Duration of acute edema ranges from hours to days, with an average of 2 days and spontaneous resolution.
- Edema episodes occur 3–4 times a year early in the disease, tend to occur less frequently with time, and eventually enter a quiescent phase.
- Reported triggers include upper respiratory infection, allergies, bee stings, emotional stress; most cases have no identifiable trigger (Browning, J Cutan Pathol 2017).
Clinical features
- Of 30 patients with blepharochalasis treated at Moorfields Eye Hospital in London, England, 14 were unilateral and 16 bilateral (Collin, OPRS 1991).
- Eyelid skin becomes atrophic, discolored, redundant, and wrinkled with recurrent attacks of inflammatory edema of the eyelids.
- Two classic subtypes: a hypertrophic (intumescent) form with orbital fat herniation/prolapse and an atrophic form with fat atrophy.
- Other sequelae can include blepharoptosis, herniation of the lacrimal gland palpebral lobe, and increased eyelid vascularity.
- In late stages, dehiscence of the upper and lower lids from the medial and lateral tendons can lead to acquired blepharophimosis.
Testing
- Biopsy of eyelid yields characteristic findings:
- Atrophy, fragmentation, and decreased/loss of dermal elastin fibers.
- Epidermis can be atrophic or thinned.
- Perivascular infiltrates composed of lymphocytes, histiocytes, plasma cells, mast cells and occasional eosinophils
- Immunofluorescence: IgA antibodies directed against elastin fibers, without IgG or IgM; however, can also be IF-negative.
- In late phases, though there can be significant loss of elastin in the eyelid skin, there can still be IgA deposits around the remaining elastin fibers (Fuchs, Br J Dermatol 1996).
- The loss of elastin is not due to reduction in production by fibroblasts.
- Reverse transcriptase polymerase chain reaction performed on eyelid skin with marked loss of elastin still shows fibroblasts expressing normal levels of mRNA for elastin production (Kaneoya, J Dermatol 2005).
Staging
- No formal severity grading, but the disease is described in active (early) and quiescent (late) stages.
- Active phase can be subdivided into intumescent vs atrophic stages.
Risk factors
- Mostly sporadic disease with some genetic predisposition
- Most cases have no known triggers, but risk factors such as URI, bee sting, stress/crying, and allergies have been reported.
Differential diagnosis
- Allergic recurrent angioedema (Garcia-Ortega, Allergy 2003)
- Blepharochalasis is easily mistaken for recurrent allergy and many patients undergo skin and patch testing and even allergy shots unnecessarily.
- The absence of systemic involvement including swelling of the extremities, pruritis, or urticaria should suggest the diagnosis.
- Unlike blepharochalasis, allergic angioedema typically involves both upper and lower lids and usually responds to antihistamines and corticosteroids.
- Hereditary angioedema is a rare, life-threatening disorder that is important to differentiate from blepharochalasis (Walford, Ann Asthma Allerg Immunol 2014).
- Specifically associated with decreased C1 esterase inhibitor activity
- Further subdivided into quantitative decrease in enzyme level (type 1, about 85% of cases) versus qualitative decrease in activity (type 2, about 15%).
- Recurrent episodes of angioedema broadly affect the subcutaneous and mucosal surfaces of the face, extremities, gastrointestinal and genitourinary tracts, and oropharynx.
- Laryngeal involvement can be fatal.
- Mean age at onset is similarly 8–12 years.
- Episodes are more frequent than blepharochalasis, every 2–5 days if untreated.
- Attacks last longer than allergic or idiopathic recurrent angioedema, typically 72–96 hours.
- There is no response to antihistamines or corticosteroids.
- The edema is nonpitting with no urticaria.
- Inherited as autosomal dominant, some have no family history
- Serum C4 levels are low, in contrast to normal levels with allergic angioedema (normal C4 during an attack essentially rules out the diagnosis of hereditary angioedema).
- Subcutaneous ecallantide is approved by the FDA for treatment of acute attacks of hereditary angioedema.
- An inhibitor of the protein kallikrein, the usual target of C1 esterase inhibitor
- Kallikrein is a protease that converts kininogen to bradykinin, which leads to fluid leakage from blood vessels.
- Dermatochalasis: seen in older people with redundant eyelid skin
- Contact dermatitis: Leading cause of eyelid dermatitis; consider allergic patch testing.
- Aponeurotic or mechanical ptosis
- Floppy eyelid syndrome
- Melkersson-Rosenthal syndrome:
- Recurrent triad of recurring oro-facial swelling, relapsing facial nerve palsy and lingua plicata
- Sarcoidosis: Isolated upper lid swelling; distinguished by noncaseating granulomas
- Sjogren syndrome: Sicca symptoms, ANA/SSA-Ro, lymphocytic sialadenitis
- Graves/thyroid eye disease: periorbital edema
Patient management: treatment and follow-up
Natural history
- Develops usually insidiously in childhood/early puberty.
- Two stages have been recognized: Active (early) stage – subdivided into intumescent (hypertrophic) and atrophic forms – and a quiescent (late) stage.
Medical therapy
- Systemic and topical corticosteroids, and antihistamines, have not proven efficacious.
- Doxycycline: Matrix metalloproteinases (notably MMP-3 and MMP-9) are released in eyelid inflammation, leading to breakdown of elastin and collagen fibers. Doxycycline inhibits MMP synthesis. Two cases of blepharochalasis, a 16- and 21-year-old, both with recent onset disease, remained symptom-free for 18 months and 10 months, respectively, after treatment with doxycycline (Karaconji, OPRS 2012).
- Oral acetazolamide (250 mg SR daily) in combination with hydrocortisone cream has been used in a small case series of six adult (37-78 years old) patients with reported efficacy(37-78 years old) (Drummond, Orbit 2009).
Radiation
- None
Surgery
- Most recommend waiting until after active phase, if possible
- Recommend quiescence for minimum of 12 months
- Ptosis correction (with lid crease formation)
- Blepharoplasty for redundant skin
- Resuspension of prolapsed lacrimal gland
- Repair of dehisced medial and lateral tendons
Other management considerations
- The presence of IgA around elastin fibers suggests an immune mechanism — and immune modulators might be of benefit — or the IgA deposition might be an epiphenomenon.
- The primary etiology of this disease is still not known.
Common treatment responses, follow-up strategies
- There is no specific treatment for this disease, other than reversing its effects once it is stable.
- If possible, avoid allergens and other triggering factors.
Preventing and managing treatment complications
Lid retraction with lagophthalmos can occur after ptosis and blepharoplasty surgery because of extreme tissue laxity and scarring.
If blepharoplasty is indicated, remove fat sparingly because the late phase of the disease is associated with fat atrophy.
Disease-related complications
- Atrophy of eyelid structures
- Prominent eyelid vascularity
- Keratopathy due to eyelid malposition, lagophthalmos and misdirected eyelashes
Historical perspective
Blepharochalasis was first described by Fuchs in 1896 as recurrent episodes of painless eyelid edema and thinning of the skin (Wien Klin Wchnschr. 1896;9:109).
In 1920, Ascher described a syndrome of blepharochalasis together with a double lip (mostly the upper lip) and nontoxic goiter (Klin Monatbl Augen 1920; 65:86; Br J Plast Surg 1981; 34:31).
References and additional resources
- AAO, Basic and Clinical Science Course. Section 7: Orbit, Eyelids, and Lacrimal System, 2010-11.
- Ascher KW: Blepharochalasis mit struma and doppellipe. Klin Monat Augen 1920; 65:86.
- Bartley GB, Gibson LE, Blepharochalasis associated with dermatomyositis and acute lymphocytic leukemia. Am J Ophthalmol 1992; 113:727.
- Benedict WL. Blepharochalasis. JAMA. 1926; 87: 1735-1739.
- Bergin DJ, McCord CD, Berger T, et al. Blepharochalasis. Br J Ophthalmol 1988; 72:863.
- Browning RJ, Sanchez AT, Mullins S, Sheehan DJ, Davis LS. Blepharochalasis: something to cry about. J Cutan Pathol. 2017;44(3)279-82.
- Collin JR. Blepharochalasis. A review of 30 cases. Ophthal Plast Reconstr Surg 1991; 7:153.
- Custer PL, Tenzel RR, Kowalczyk AP. Blepharochalasis syndrome. Am J Ophthalmol 1985; 99:424-428.
- Drummond SR, Kemp EG: Successful medical treatment of blepharochalasis: a case series. Orbit 2009; 28:313.
- Frigas E, Park M. Idiopathic recurrent angioedema. Immunol Allergy Clin North Am. 2006;26:739-751.
- Fuchs E. Ueber Blepharochalasis. Wien Klin Wchnschr. 1896;9:109.
- Garcia-Ortega P, Mascaro F, Corominas M, Carreras M: Blepharochalasis misdiagnosed as allergic recurrent angioedema. Allergy 2003; 58:1197.
- Grassegger A, Romani N, Fritsch P, et al. Immunoglobulin A (IgA) deposits in lesional skin of a patient with blepharochalasis. Br J Dermatol 1996;135:791.
- Hallahan KM, Sood A, Singh AD: Acute episode of eyelid oedema. Br J Ophthalmol 2012; 96:909.
- Huemer GM, Schoeller T, Wechselberger G, et al. Unilateral blepharochalasis. Br J Plast Surg 2003; 56:293.
- Hundal KS, Mearza AA, Joshi N. Lacrimal gland prolapse in blepharochalasis. Eye 2004; 18:429-430.
- Jordan DR. Blepharochalasis syndrome: a proposed pathophysiologic mechanism. Can J. Ophthalmol 1992; 27:10.
- Kaneoya K et al. Elastin Gene Expression in Blepharochalasis. J Dermatol 2005; 32:26
- Karaconji T, Skippen B, Di Girolamo N, et al: Doxycycline for treatment of blepharochalasis via inhibition of matrix metalloproteinases. Ophthal Plast Reconstr Surg 2012; 28:e76.
- Koursh MD, Modjtahedi SP, Selva D, Leibovitch I. The blepharochalasis syndrome. Surv Ophthalmol 2009; 54:235.
- Langley KE, Patrinely JR, Anderson RL, Thiese SM. Unilateral blepharochalasis. Ophthalmic Surg 1987;18:594.
- Li D, Chen T, Hou Z, Li Y: Clinical features of blepharochalasis and surgical treatment of associated deformities. Chinese J Ophthalmol 2012; 48:696.
- Rintala AE: Congenital double lip and Ascher syndrome: II. Relationship to the lower lip sinus syndrome. Br J Plast Surg 1981; 34:31.
- Tenzel RR, Stewart WB: Blepharo-confusion: blepharochalasis or dermatochalasis. Arch Ophthalmol. 1978;96:911.
- Walford HH, Zuraw BL: Current update on cellular and molecular mechanisms of hereditary angioedema. Ann Asthma Allerg Immunol 2014; 112:413.
- Wang G, Li C, Gao T: Blepharochalasis: A rare condition misdiagnosed as recurrent angioedema. Arch Dermatol 2009; 145:498.
Financial disclosures
Reviewers
Eva Chou: None